Common Registration Assessment, Part 1
Methotrexate weekly dose calculations
Three original questions on once-weekly methotrexate doses and tablet counts, with the working shown.
Published 14 October 2026. Independent revision material, not GPhC questions, not for patient care.
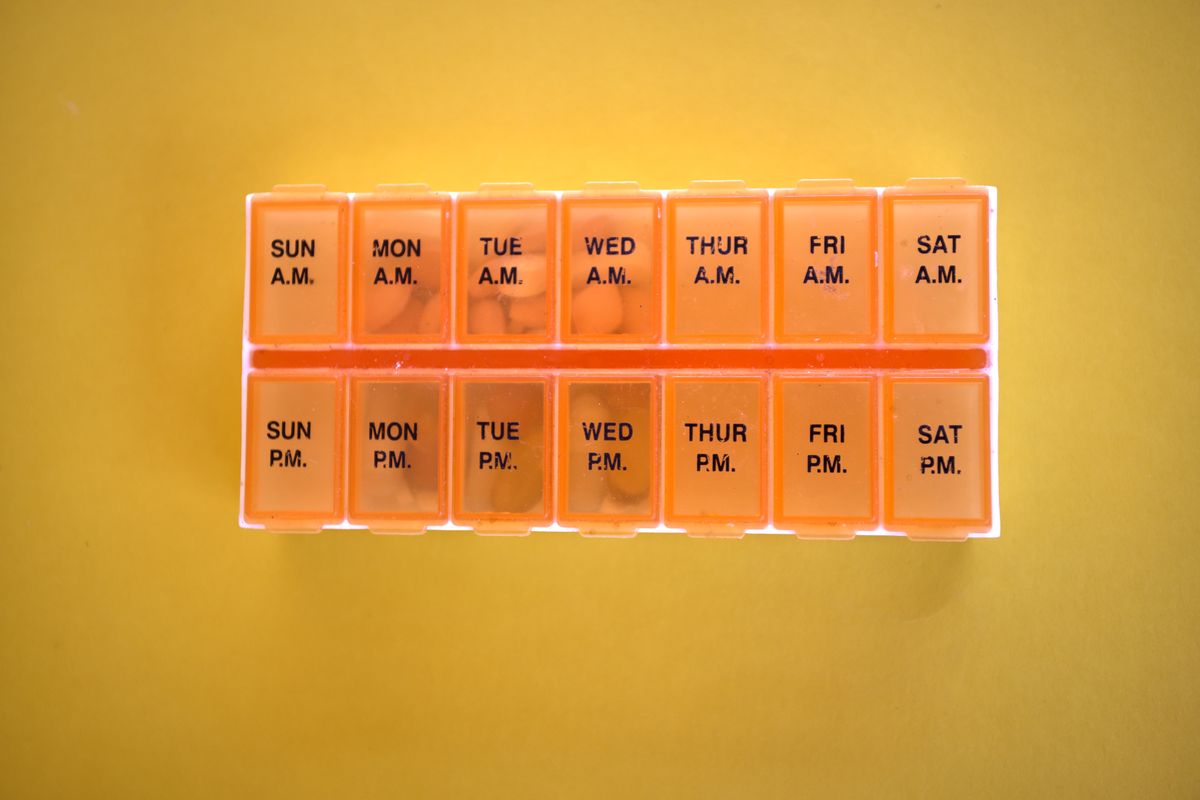
Methotrexate for autoimmune disease is taken once a week. The MHRA Drug Safety Update of September 2020 reports serious toxicity from daily dosing by mistake, and advises dispensers to remind the patient of weekly dosing and to write the day of the week on the pack where there is space.
The emc SmPC for methotrexate 2.5 mg tablets gives an initial dose in rheumatoid arthritis of 7.5 mg once weekly, not to exceed 20 mg a week, and 10 to 25 mg once weekly for severe psoriasis. These are non-cancer uses only. The BNF methotrexate entry still carries the 2020 MHRA advice and recommends that only one strength of tablet, usually 2.5 mg, is prescribed and dispensed. The Pharmaceutical Journal reported on 19 December 2025 that the GPhC reminded pharmacy teams to supply methotrexate in line with that 2020 update. The calculations here are tablet counts and weekly totals.
The method
- Write the weekly dose in mg and the tablet strength in mg.
- Divide the dose by the tablet strength to get tablets per week.
- Multiply by the number of weeks for a supply, or divide the pack size by tablets per week to find how many weeks a pack lasts.
- To size a daily dosing error, multiply the dose given each day by 7 and compare with the weekly dose.
- State the day of the week on the label, never a daily instruction.
Three practice questions
Work each one on paper first, then open the answer. All patients and prescriptions are fictional.
Question 1
A patient has methotrexate 7.5 mg once weekly using 2.5 mg tablets. How many tablets is one dose, and how many for 4 weeks?
Show the answer
Answer: 3 tablets per dose, 12 tablets for 4 weeks
Working: 7.5 ÷ 2.5 = 3 tablets once a week. 3 × 4 = 12 tablets.
Question 2
The same patient takes 3 tablets every day for a week by mistake. How many mg is that, how many times the intended weekly dose, and what should the patient be told to do?
Show the answer
Answer: 52.5 mg, which is 7 times the intended dose. This is a serious medication error: the patient should seek urgent medical attention.
Working: Per day: 7.5 mg. Over 7 days: 7.5 × 7 = 52.5 mg. 52.5 ÷ 7.5 = 7 times. The MHRA Drug Safety Update says patients should seek urgent medical attention if they think they have taken too much methotrexate. The arithmetic only sizes the error; the clinical response comes from a prescriber or emergency service, not from this page.
Question 3
A patient has 10 mg once weekly using 2.5 mg tablets, supplied in a pack of 28 tablets. How many tablets per dose, and how many weeks does a pack last?
Show the answer
Answer: 4 tablets per dose, and 7 weeks
Working: 10 ÷ 2.5 = 4 tablets a week. 28 ÷ 4 = 7 weeks.
Exam approach
Convert the weekly dose to tablets, then scale by weeks. For an error, multiply the dose by the number of days taken.
Where marks are lost
- Reading 'once weekly' as a daily dose.
- Mixing up 2.5 mg and 10 mg tablets when converting mg to tablets.
- Forgetting that the maximum weekly dose in the SmPC for rheumatoid arthritis is 20 mg.
- Leaving the day of the week off the label.
- Treating a daily dosing error as an arithmetic exercise only: the patient needs urgent medical attention.
Frequently asked questions
What did the MHRA advise dispensers about once-weekly methotrexate?
The Drug Safety Update says to remind the patient of the once-weekly dosing and the risk of fatal overdose if they take more than directed, and to write the day of the week on the outer package where there is space.
How many 2.5 mg tablets make 20 mg?
20 ÷ 2.5 = 8 tablets. The SmPC says the weekly total in rheumatoid arthritis should not exceed 20 mg.
Sources
- MHRA, methotrexate once-weekly for autoimmune diseases (Drug Safety Update, 23 September 2020)
- emc, methotrexate 2.5 mg tablets SmPC (last updated 16 September 2026)
- BNF, methotrexate
- The Pharmaceutical Journal, GPhC writes to pharmacy teams after methotrexate dispensed with instruction to take once daily (19 December 2025)
- GPhC, Common Registration Assessment specification and permitted items for 2026
The questions above are original and use fictional patients and prescriptions. PreRegExamPrep is not affiliated with or endorsed by the General Pharmaceutical Council.
Practise until the method is automatic
Try 15 free questions with worked answers. No sign-up required.
More calculation topics
- Dose by weight calculations for the GPhC assessment
- Volume to give: liquid medicine calculations
- Percentage strength calculations: w/v, w/w and ratios
- Dilution calculations with C1V1 = C2V2
- Infusion rate calculations in mL per hour
- Drip rate calculations: drops per minute
- Body surface area calculations
- Creatinine clearance (Cockcroft-Gault) calculations
- Moles and millimoles calculations
- Displacement volume calculations for reconstitution
- Quantity to supply calculations
- Using a provided formula in calculations
- Dose information from packaging and labels
- Diluting a stock to a lower strength
- Medicine cost and switch calculations
- Rounding rules in calculations
- Enteral feed rate calculations
- Electrolyte content over time
- Infusion dose per kg per hour
- Rounding doses to measurable volumes
- Relative risk and relative risk reduction
- Absolute risk reduction and number needed to treat
- Odds ratio and confidence intervals
- Relative versus absolute risk reduction
- Loading dose and volume of distribution
- Top-up doses from measured drug levels
- Salt correction factors
- Mass and molar drug concentrations
- Half-life and falling drug levels
- Steady-state concentration and infusion rate
- Bioavailability and equivalent oral doses
- Oral maintenance dose and dosing interval
- Elimination rate constant and half-life
- Accumulation towards steady state
- Ratio strengths and one in X
- Serial dilution factors
- Mixing solutions of different strengths
- Tablet quantities for reducing regimens
- Equivalent doses from provided conversion tables
- Thresholds and dose-banding algorithms
- Unit conversions for mass and volume
- Units and units per mL
- Reconstituting powders and final concentration
- Millimoles and milliequivalents
- Infusion time and volume remaining
- Days supply from pack sizes
- Percentage w/v and w/w conversions
- Ideal and adjusted body weight from formulae
- Diluting creams and ointments by weight
- Scaling a formula to a batch size
- Age-band doses from a provided table
- Tablet fractions and split doses
- Stones, pounds, inches and metric conversions
- Micrograms per minute from mg per hour
- Percentage change and mark-up
- Molar solutions and mass per volume
- Osmolarity from component concentrations
- Direct proportion and cross-multiplication
- Scientific notation and very small quantities
- Stock use and reorder quantities
- Parts per million and very dilute solutions
- Sodium chloride equivalents and isotonic solutions
- Density and specific gravity conversions
- Doses per day and hours between doses
- Finding the volume of diluent to add
- Capping a dose at a stated maximum
- Whole vials and ampoules to draw up
- Reading values from a provided graph
- Micrograms per kg per minute infusions
- Percentage composition of a compound preparation
- Suppository displacement values
- Isotonicity by freezing point depression
- Energy content of parenteral nutrition
- Syringe driver rate calculations
- Area under the curve calculations
- Renal dose adjustments using provided bands
- Insulin units and infusion calculations
- Working backwards from a stated dose
- Doses and days from multi-dose devices
- Combined additives in one infusion
- BMI calculations for the GPhC assessment
- Fewest tablets to make a dose
- Clearance from half-life and volume of distribution
- Maintenance fluid requirements by weight
- Sodium load from effervescent tablets
- Ethanol content of liquid preparations
- Oxygen cylinder duration calculations
- Urine output and fluid balance calculations
- Quantities for titration packs
- Infusion line priming and dead space
- Alcohol unit calculations for the GPhC assessment
- Paracetamol syrup calculations for children
- Ibuprofen liquid calculations for children
- Vitamin D conversions for the GPhC assessment
- Ferrous sulfate drops and tablet calculations
- Amoxicillin liquid and capsule calculations
- Folic acid dose and quantity calculations
- Adult paracetamol and the daily maximum
- Calcium and iron intake calculations
- Salt limit calculations by age
- Fingertip unit calculations for the GPhC assessment
- Adrenaline dose calculations for anaphylaxis
- Breakthrough opioid dose calculations
- IV fluid bolus calculations in children
- Neonatal maintenance fluid calculations
- Enoxaparin dose calculations by weight
- Levothyroxine dose by weight calculations
- Sensitivity, specificity and predictive value calculations
- Hypertonic saline bolus calculations in children
See also the formula sheet, the eight sample questions and the approved calculator page.